
Restoring healthy oxygen levels in newborns
High-Frequency Ventilation for Newborns
High-frequency ventilation is an advanced form of respiratory support used in selected critically ill newborns when conventional respiratory support may not be sufficient or appropriate. Treatment is individualised according to the baby’s lung condition, gestation and clinical response.
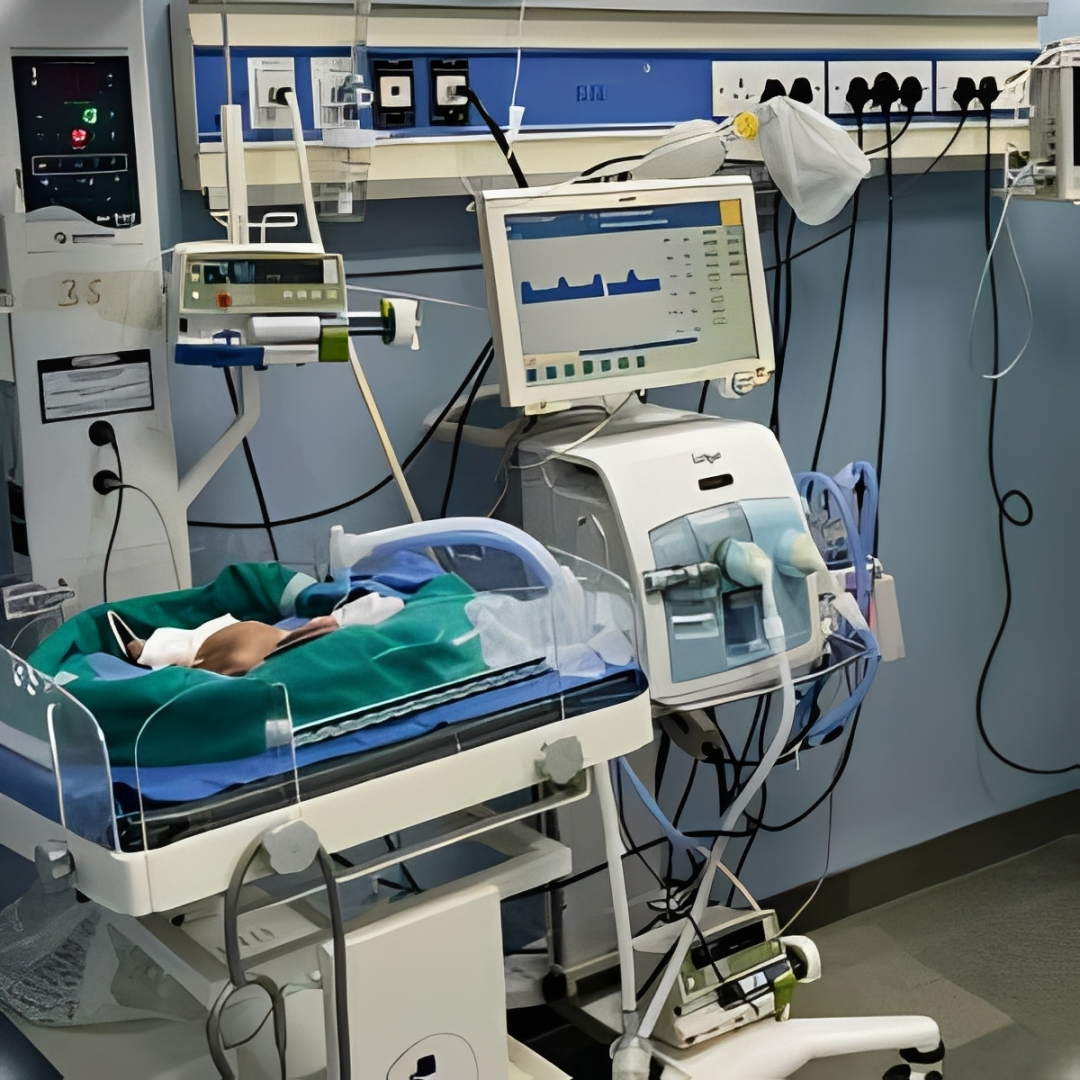
Indications for HFOV
Severe respiratory distress syndrome not responding to conventional ventilation
Meconium aspiration syndrome with air trapping
Persistent pulmonary hypertension of the newborn, often combined with iNO therapy
Pulmonary interstitial emphysema and other air-leak syndromes
Severe pneumonia or sepsis-related lung injury
Congenital diaphragmatic hernia needing lung-protective ventilation
Extreme prematurity with stiff, poorly compliant lungs
Rising oxygen or pressure needs despite maximal conventional settings
How it works
A continuous distending pressure holds the lung open, while an oscillator layers rapid, tiny breaths on top of it.
It is used as rescue support when conventional ventilation is failing, and sometimes from the outset for the most vulnerable babies.
Conventional ventilators cycle larger volumes of air in and out at normal breathing rates. In a lung that’s already stiff, inflamed or underdeveloped, these larger swings in pressure and volume can cause further injury. HFOV ventilation uses smaller, rapid breaths at lower pressures to provide respiratory support while helping reduce lung injury.
HFOV instead holds the lung open at a steady mean airway pressure and layers extremely rapid, very small oscillations — often 300 to 900 times a minute — on top of it. Gas exchange happens through this continuous, gentler pattern rather than through big in-and-out breaths.
Advanced Neonatal Capabilities
iNO
Therapy
aEEG / CFM
Monitoring
Therapeutic Hypothermia
HFO / HFOV
Ventilation
Therapeutic
Hypothermia
aEEG / Brain
Monitoring
Advanced Neonatal Critical Care, Patiala
Dr. Vivneet's Vardaan Hospital runs a Level III NICU built for babies who need more than routine newborn care.
- Level III NICU with 24×7 neonatal critical care
- iNO therapy for pulmonary hypertension
- aEEG / CFM brain-function monitoring
- Conventional and HFO/HFOV ventilation
- Therapeutic hypothermia for birth asphyxia
- Cashless treatment under applicable government schemes